



 Spanish (pdf)
 Article in xml format
 Article references

 Automatic translation
 Send this article by e-mail
 Cited by SciELO
 Similars in
SciELO

 Permalink


INTRODUCTION
Maternal mortality (MM) is defined “as the death of a woman during pregnancy, child birth or within 42 days after termination of pregnancy, due to any cause related to or aggravated pregnancy”1. It constitute some of the most sensitive social and health indicators, since each maternal death brings with it a cascade of consequences that directly impact various levels, such as the family, society and health systems. Therefore, it continues to be a global public health problem, especially in low-and middle-income countries2-4. For this reason, it is part of the commitments of the Sustainable Development Goals (SDG)5 and countries have committed to reducing the MM ratio to less than 70 per 100,000 live births by 20306.
Worldwide, during 2015, MM were estimated at 303,000 cases, of which 99 % occurred in low- and middle-income countries. In the Americas region, the average MM ratio was 67 per 100,000 live births in 2017, but with wide disparities between countries, from less than 10 per 100,000 in Canada and the United States, to 476 per 100,000 in Haiti. Globally, the main direct causes are hemorrhage (27 %), hypertensive disorders (14 %), sepsis (11 %), unsafe abortions (8 %) and obstructed labor (5 %)2,7.
Paraguay, during the years 2008 to 2018, has managed to reduce MM, going from a ratio of 117 to 71 per 100,000 live births8. However, this progress has not been equitable, with higher mortality being recorded in some regions of the country. In 2018, seven departments accounted for 79 % of maternal deaths, with variations of up to 4 times greater between regions3. Analysis of trends and disparities in MM by region and age group is essential to target interventions and accelerate progress toward national health goals9.
The COVID-19 pandemic has had a strong impact on pregnant women, increasing the risk of MM. Recently, a multicenter study carried out between March 2020 and November 2021 in 8 Latin American countries described the characteristics of 447 maternal deaths associated with SARS-Cov-2 infections confirmed by PCR. An alarming fact was that 35 % of the deceased did not have Access to intensive care units, highlighting important barriers to Access to critical services for pregnant women in the region10-12.
The present study provide an updated analysis of the maternal mortality situation in the country from 2014 to 2021, identifying patterns, regional disparities and higher risk groups; providing key inputs for decision-making in public policies and the strengthening of maternal health programs, therefore the objective of the present study is to describe the characteristics of MM in Paraguay during the period from 2014 to 2021.
METHODOLOGY
A descriptive, cross-sectional, retrospective study was carried out using the death certificate records of the General Directorate of Strategic Health Information (DIGIES) of the Ministry of Public Health and Social Welfare (MSP and BS) of Paraguay, the official institution responsible for national health and disease statistics13. The geographical scope was the 18 Health Regions including Asunción and the temporal scope considered was from 2014 to 2021.
The sampling was non-probabilistic, of consecutive cases. The study population was all maternal deaths registered in Paraguay in the study period.
The variables were classified into sociodemographic variables (age, lifecycle, educational level and marital status) and variables related to the characteristics of maternal mortality (year, basic cause of death, type of institution and professional who certified the death). The ages soft he mothers were also grouped by life cycle, being adolescents (13 to 19 years), Young adults (20 to 25 years), adults (26 to 44 years) and late adults (45 to 51 years).
The MM ratio was calculated, which consisted of the number of maternal deaths per-100,000 live births. In addition, frequencies expressed in percentages were calculated. Data were analyzed with Microsoft Excel® and Epi-Info7 version 7.2.1.1.
Regarding ethical criteria, since it is a research with anonymized secondary data source without the participation of human beings, the protocol of this work did not require the approval of the Research Ethics Committee.
RESULTS
During the period from 2014 to 2021, 740 cases of maternal deaths were recorded, with an average maternal mortality ratio of 83.91 deaths per 100,000 live births. The year with the lowest MM ratio was 2014, with 63.92, and the year with the highest ratio was 2021 with 159.98 (Table 1).
Table 1: Annual distribution of maternal mortality, Paraguay (2014 - 2021)
| Year | Numberof MM | Numberoflivebirths | Percentageof MM | Ratio of MM/1,000 live births |
|---|---|---|---|---|
| 2014 | 72 | 112646 | 9,73 | 63,92 |
| 2015 | 95 | 116181 | 12,84 | 81,77 |
| 2016 | 96 | 111146 | 12,97 | 86,37 |
| 2017 | 78 | 115895 | 10,54 | 67,30 |
| 2018 | 79 | 111642 | 10,68 | 70,76 |
| 2019 | 73 | 107911 | 9,86 | 67,65 |
| 2020 | 81 | 102722 | 10,95 | 78,85 |
| 2021 | 166 | 103766 | 22,43 | 159,98 |
| Total | 740 | 881,909 | 100,00 | 83,91 |
Source: Vital Statistics Information Sub-System (SSIEV). Dept. of Biostatistics-DIGIES-MSP and BS. Asunción, Paraguay (2014 - 2021).
Regarding age, 49.38 % (364) of the deaths corresponded to women under 30 years of age, with the highest number of deaths occurring in the age group of 30 to 34 years (22.43 %, 166). It is worth mentioning the maternal deaths that appear at the extremes of life: 0.81 %6 in women under 15 years of age and 0.27 %2 in women over 50 years of age. Considering the life cycle, 28.11 % (208) of the deaths occurred in adulthood. Regarding educational level, 18.65 % (138) of the mothers had completed primary school, and 58.11 % (430) were single (Table 2).
Table 2: Sociodemographic characteristics of the mothers, Paraguay (2014 - 2021)
| Sociodemographic Variables Age | Frequency | Percentage |
|---|---|---|
| <15 | 6 | 0,81 |
| 15-19 | 90 | 12,16 |
| 20-24 | 128 | 17,30 |
| 25-29 | 140 | 18,92 |
| 30-34 | 166 | 22,43 |
| 35-39 | 133 | 17,97 |
| 40-44 | 62 | 8,38 |
| 45-49 | 13 | 1,76 |
| >50 | 2 | 0,27 |
| LifeCycle | ||
| Teenagers | 96 | 12,97 |
| Youth | 434 | 58,65 |
| Adult | 208 | 28,11 |
| Late adult | 2 | 0,27 |
| Educationallevel | ||
| None | 40 | 5,41 |
| Incompleteprimary | 116 | 15,68 |
| Complete primary | 138 | 18,65 |
| Basic SchoolEducation | 80 | 10,81 |
| Complete secondaryschool | 87 | 11,76 |
| Complete University or Higher Education | 68 | 9,19 |
| Don'tknow | 121 | 16,35 |
| Marital status | ||
| Single | 430 | 58,11 |
| United | 164 | 22,16 |
| Married | 122 | 16,49 |
| Don'tknow | 20 | 2,70 |
| Widow | 2 | 0,27 |
| Separate | 1 | 0,14 |
| Divorced | 1 | 0,14 |
Source: Vital Statistics Information Sub-System (SSIEV). Dept. of Biostatistics-DIGIES-MSP and BS. Asunción, Paraguay (2014 - 2021).
Among the basic causes of death, the main ones were complications of pregnancy, childbirth and the postpartum period (22,43 %, 166) and Diseases of the Respiratory System (18,11 %, 134) and toxemia (15,81 %, 117). 63,65 % (471) of the deaths occurred in an MSP and BS institution, and the non-treating physician was the most frequent professional who certified the death (59,19 %, 438) (Table 3).
Table 3: Characteristics of maternal mortality in Paraguay (2014 - 2021)
| Characteristics Basic cause of death | Frequency | Percentage |
|---|---|---|
| Diseases of the Respiratory System. | 134 | 18,11 |
| Toxemia | 117 | 15,81 |
| Hemorrhage | 89 | 12,03 |
| Abortion | 85 | 11,49 |
| Other maternal infectious and parasitic diseases | 57 | 7,70 |
| Diseases of the Circulatory System. | 37 | 5,00 |
| Sepsis | 28 | 3,78 |
| Diseases of the DigestiveSystem. | 14 | 1,89 |
| HIV virus disease | 13 | 1,76 |
| Other complications of pregnancy, child birth and the post partum period | 166 | 22,43 |
| Typeofinstitution | ||
| Institutionof MSP and BS | 471 | 63,65 |
| Instituteof Social Security | 79 | 10,68 |
| Privateinstitution | 60 | 8,11 |
| Home | 61 | 8,24 |
| Street | 19 | 2,57 |
| Other | 50 | 6,76 |
| Typeofprofessional | ||
| Treating doctor | 254 | 34,32 |
| Non-treatingphysician | 438 | 59,19 |
| Medical examiner | 37 | 5,00 |
| Authorizedhealthpersonnel | 11 | 1,49 |
Source: Vital Statistics Information Sub-System (SSIEV). Dept. of Biostatistics-DIGIES-MSP and BS. Asunción, Paraguay (2014 - 2021).
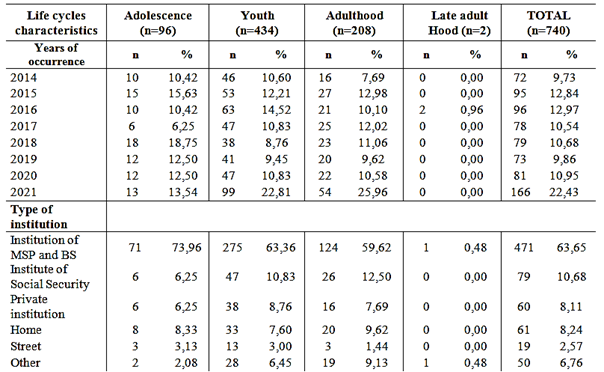
When analyzing the life cycle in relation to the years of occurrence, it is observed that, in all years, the majority of deaths from all causes occurred in youth and adulthood. Similarly, the highest proportion of maternal deaths occurred most frequently in institutions of the Ministry of Public Health and Social Welfare (MSP and BS), followed by those of the Institute of Social Security (IPS) (Table 4).
Table 4: Characteristics of maternal mortality in Paraguay (2014 - 2021)
Source: Vital Statistics Information Sub-System (SSIEV). Dept. of Biostatistics-DIGIES-MSP and BS. Asunción, Paraguay (2014 - 2021).
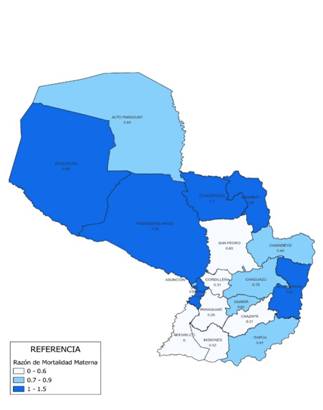
The maternal mortality ratio in Paraguay during the period 2014-2021 shows notable differences between health regions. Concepción leads with the highest rate of 1.40 deaths per 100,000 live births, followed by Presidente Hayes with 1.36 and Central with 1.27. Other regions with high rates include Alto Paraná (1.02) and Amambay (1.04). At the other extreme, Ñeembucú did not report maternal deaths during this period, and Paraguarí presented a low rate of 0.26 (Figure 1).
DISCUSSION
During the period 2014-2021, Paraguay recorded 740 maternal deaths, with an average ratio of 84 deaths per 100,000 live births. The annual analysis of the figures reveals significant fluctuations, with 2014 being the year that presented the lowest MM ratio with 63.92 deaths per 100,000 live births, which could be related to more effective health policies implemented in that period and are coincident. with previous studies carried out by Mora-Escobar et al.8, who documented during the years 2008 to 2018 (pre-pandemic period) a decrease in the MM ratio from 117 to 71 per 100,000 live births. Before the pandemic, the goal was reached for the MMR to be less than 70, fulfilling the goal of “no one being left behind,” which is one of the goals of the SDGs13. The MMR obtained for the years 2015, 2016, 2017 and 2018 coincide with previous work on this topic, which indicates the consistency of these results14.
At the regional level, comparing these findings with similar studies, in Colombia during the period 2016 to 2020 the MM ratio fluctuated between 54.3 and 70.2 per 100,000 live births, presenting lower figures tan those reported in Paraguay during the same period. This suggests that although both countries face similar challenges in terms of access to health care, regional disparities and socioeconomic conditions influence outcomes15.
During recent years, a constant increase in mortality was observed, ending 2021 with a MM ratio of 159.98. Compared to other countries in the region, the behavior of maternal mortality in Paraguay during the pandemic was similar to that of Bolivia15. According to Montoya et al., Bolivia also experienced an increase in maternal mortality during the pandemic years, with an average ratio of 115 deaths per 100,000 live births between 2015 and 2020. These data suggest that the global health crisis affected similarly to countries with greatest challenges in terms of access to health services and resources, reflecting how the pandemic significantly impacted the progress made, under lining the vulnerability of the health system in times of crisis, suggestingtheneedtoreinforcepublichealthstrategiestoprevent future setbacks. The COVID 19 pandemic disproportionately affected pregnant women and exacerbated pre-existing inequalities in access to health services.
The inequalities in health care in Paraguay have already been pointed out by Tulloet. al3 which mentions that the barriers in accessing maternal health services were particularly pronounced in rural regions and areas with less health infrastructure. These disparities, exacerbated during the pandemic, may have contributed to the alarming increase in maternal mortality observed in recent years.
Departmental gaps are important. The Departmentof Ñeembucú presented on average 0 notifications of MM, which should be investigated if these mortalities really did not exist, were not notified or the deaths occurred in another Department other tan the maternal residence. The Departments of Alto Paraná and Concepción exceed the ratio of 70 MM expected to comply with the SDGs13. These results are to be expected, since the Central Department is the most populated Department in the country. The Central Department and Asunción concentrate 37.75 % of the country's total population, which represents 2,807,111 inhabitants16. Meanwhile, the Alto Paraná department for the year 2021 had 842,307 inhabitants (11.5 % of the country's total population), thus becoming the third most populated Department16.
According to the World Bank, Paraguay is the third country with the lowest Gross Domestic Product (GDP) per capita in the Region and ranks third among the countries with the greatest inequalities at the regional level17. One of the reasons for this inequality lies in the unequal distribution of income among the population, which translates into a low quantity and quality of social investment, particularly in childhood, excluding the population from accessing social services. Basic health, drinking water, sanitation, education, housing, food and nutrition18.
Women aged 30 to 34 years presented 22.43 % (166) of the deaths, which coincides with an investigation carried out in Ethiopia where a similar prevalence was found, indicating that this trend could be common in different geographical and economic contexts19.
An important aspect to highlight are deaths at the extremes of life, with 0.81 % (6 cases) in adolescents aged 13 to 14 years and 0.27 % (2 cases) in women over 50 years of age. Although these percentages are relatively low, they reflect the vulnerability of extreme age groups. This finding is consistent with a study conducted in Nigeria, where adolescent girls and older women faced a significantly increase drisk of complications during pregnancy and child birth, highlighting the need for targeted interventions for these groups20.
The life cycle also shows that 58.64 % of deaths occurred in youth, which underlines the importance of concentrating prevention and care efforts at this stage. Regarding educational level, 18.65 % of the deceased mothers had completed primary school and 15.68 % had only completed incomplete primary school. According to data from the National Institute of Statistics (INE), on average mothers have attended 9.3 years in a formal educational institution, reaching 10.3 years in urban areas while in rural areas it reaches at 7.6 years of study21.
This finding is consistent with studies conducted in countries such as India, where low educational attainment has been shown to be associated with a higher risk of maternal mortality due to limited access to health services and a lowerability to make informed decisions about care. medical22. Women's education constitutes one of the social determinants of health, which has been shown to have a consistent association with the use of health services by mothers. Furthermore, studies have shown that husband's education increases women's use of services23. In a work carried out in Ecuador, it was observed that five socioeconomic indicators demonstrated to be statistically significant with the RMM; the general fertility rate, percentage of indigenous population, percentage of households with children who do not attend school, the Gross Domestic Product (GDP) and the percentage of households with electricity14.
Marital status also emerged as a relevant factor, with 58.11 % of the deceased women being single. This finding suggests that single women may face additional barriers in accessing maternal health services, which has also been observed in studies in Brazil, where single women showed greater vulnerability due to lack of social and economic support24. Added to this situation is that 37.2 % of Paraguayan households are headed by women25.
The analysis of the causes of maternal death reveals critical information about the factors that contribute to maternal mortality in the country. Excluding “other complications of pregnancy, child birth and puerperium", the main causes of death were diseases of the respiratory system, toxemia, hemorrhage, abortion, and sepsis. The high prevalence of toxemia, which includes hypertensive disorders of pregnancy such as preeclampsia and eclampsia, highlights the importance of adequate prenatal control and early detection of these disorders. These results coincide with those of Brazil, where toxemia constitutes one of the main causes of pregnancy. Death in adulthood, since it is the stage with the highest risk of serious complications26. The high prevalence of maternal mortality in pregnancies with preeclampsia emphasizes the need for close monitoring and special attention to early-onset cases27.
Abortion as a cause of maternal death is an alarming fact, especially in contexts where access to safe abortion services is limited. These figures could be higher, since in Paraguay abortion is criminalized by law, so higher figures tan those presented are to be expected. Mass contraceptive education is crucial to preventing maternal deaths from unsafe abortions, which account for around 13 % of maternal deaths annually, particularly in developing countries with limited safe reproductive services and high light the need to improve Access to health services. Reproductive health and the management of post abortion complications in this population27,28.
Hemorrhage, which represents 12.03 % of maternal deaths in Paraguay, is another significant cause that has been identified globally as a critical factor in maternal mortality. Studies in Latin America have shown that postpartum hemorrhage is one of the leading causes of death in pregnant women, and the lack of quick access to emergency care exacerbates this situation29.
Regarding sepsis, which contributed to 3.78 % of deaths, it continues to be a relevant cause, although less prevalent compared to other complications. Sepsis is a significant health burden in Latin American countries, with studies show inghigh mortality rates from septic shock ranging from 45.6 % to 51 % in Colombia and Argentina30. However, its presence underlines the importance of hygienic conditions and proper management of infections during pregnancy and the postpartum period. Maternal sepsis has been identified in other international studies as a preventable cause of death if appropriate management protocols are implemented31.
The analysis of life cycles in relation to the basic causes of maternal death in Paraguay between 2014 and 2021 reveals that the majority of deaths occurred in youth and adulthood, with 86.76% of cases in both life cycles, depending on the year.
The majority occurred in institutions of the Ministry of Public Health and Social Welfare (MSP and BS), followed by the Social Security Institute (IPS). This highlights the crucial role of public institutions in maternal health care in Paraguay, although it also highlights possible limitations in the capacity to respond to obstetric emergencies, especially in resource-limited contexts. A study in Brazil also identified that the majority of maternal deaths occurred in public institutions, suggesting that public health policies should focus on improving the quality of care in these settings26. According to data from the INE, in 2019, women registered only 28.4% of health insurance25.
In relation to the limitations of the present study, we can mention that by using secondary data, the researchers were notable to select or aggregate variables. In that sense, it would have been interesting to add more variables related to the Social Determinants of Health. As strengths we can mention the use of data collected in the Surveillance by the health authority, which is the MSP and BS.
The maternal mortality ratio in Paraguay during the period 2014-2021 shows notable differences between health regions, which highlights the variability in maternal mortality between different regions, underscoring the need for specific approaches to improve care and reduce mortality in areas with higher rates.
CONCLUSION
During the period 2014-2021, Paraguay experienced a worrying increase in the maternal mortality ratio, reaching its peak in 2021, coinciding with the impact of the COVID-19 pandemic. The majority of maternal deaths occurred in young, less educated, and single women. The most frequent causes were toxemia, abortion and hemorrhage and occurred in public institutions.

