



Servicios Personalizados
Revista

Articulo
 texto en
 Inglés (pdf)
 Articulo en XML
 Referencias del artículo

 Traducción automática
 Enviar articulo por email
Indicadores
-
 Citado por SciELO
Links relacionados
-
 Similares en
SciELO
Compartir

 Permalink

Anales de la Facultad de Ciencias Médicas (Asunción)
versión impresa ISSN 1816-8949
An. Fac. Cienc. Méd. (Asunción) vol.58 no.3 Asunción dic. 2025
https://doi.org/10.18004/anales/2025.058.03.87
CASE REPORT
Atypical Herpetic Infections in Immunocompromised Patients
1
 http://orcid.org/0000-0002-6886-6762
1
http://orcid.org/0009-0001-4270-2882
1Hospital Nacional de Itauguá. Departamento de Medicina Interna. Servicio de Dermatología. Itauguá, Paraguay.
2Hospital Nacional de Itauguá. Servicio de anatomía patológica. Itauguá, Paraguay.
Herpetic infections are caused by viruses of the Herpesviridae family. The most common are those responsible for oral herpes, genital herpes, and varicella-zoster. In immunocompromised patients, the clinical presentation may be atypical, making diagnosis difficult and leading to potentially lethal complications.
Three clinical cases of herpetic infections in immunocompromised patients are presented.
The first case involves a patient with HIV presenting with extensive ulcerative lesions. Differential diagnoses included fungal, mycobacterial, and viral infections; a diagnosis of herpes simplex virus type 2 infection was reached via molecular biology. The patient was treated with acyclovir and showed a favorable respons.
The second case describes a patient with HIV and a history of childhood varicella, presenting with sparse papulovesicular lesions distributed throughout the body. The initial suspicion was a fungal infection; however, the biopsy returned consistent with a herpes infection. The lesions resolved spontaneously without major complications, as the study results were returned late.
The third case involves a patient with systemic lupus erythematosus under immunosuppressive treatment, presenting with extensive vesiculobullous lesions on the trunk and extremities, with mucosal involvement. The initial suspicion was autoimmune bullous dermatosis, but the biopsy was consistent with a herpes infection. Due to multiorgan failure and a fatal outcome, the diagnosis was made post-mortem, and the patient did not receive specific treatment.
Keywords: viral infections; herpes virus infections; immunosuppression; case report.
Las infecciones herpéticas son producidas por virus de la familia Herpesviridae. Los más frecuentes son los que producen el herpes labial, herpes genital y varicela-zóster. En pacientes inmunodeprimidos la presentación clínica puede ser atípica, dificultando el diagnóstico y produciendo complicaciones potencialmente letales.
Se presentan 3 casos clínicos de infecciones herpéticas en pacientes inmunodeprimidos.
En el primer caso, lesiones ulcerativas extensas en un paciente portador de VIH, con diagnósticos diferenciales entre infecciones fúngicas, micobacterianas y virales, llegando al diagnóstico de infección por herpes tipo 2 mediante biología molecular. Se trató con aciclovir, teniendo una respuesta favorable.
En el segundo caso, lesiones papulovesiculares escasas distribuidas en todo el cuerpo en un paciente portador de VIH y antecedente de varicela en la infancia. La sospecha inicial fue una infección fúngica, con retorno de biopsia compatible con infección herpética. Tuvo resolución espontánea de lesiones, debido al retorno tardío del estudio, sin mayores complicaciones.
En el tercer caso, lesiones vesicoampollares extensas en tronco y extremidades, con afectación de la mucosa, en paciente con lupus eritematoso sistémico en tratamiento con inmunosupresores. La sospecha inicial fue una dermatosis ampollar autoinmune, retornando la biopsia compatible con infección herpética. Debido a la falla multiorgánica, y el desenlace fatal, el diagnostico fue post mortem y no recibió tratamiento por tal motivo.
Palabras claves: infecciones virales; infecciones por herpes virus; inmunosupresión; reporte de caso.
INTRODUCTION
Herpes infections are caused by viruses belonging to the Herpesviridae family, of which there are at least eight subtypes pathogenic to humans. Herpes simplex virus type 1, type 2, and varicella-zoster virus are the most frequent agents, causing herpes labialis, genital herpes, and varicella-zoster, respectively (1).
Herpes simplex causes cutaneous lesions on the external genitalia, perianal region, oral cavity, and lips. These begin as painful vesicles that subsequently ulcerate and resolve in approximately 15 days without treatment. In contrast, in immunocompromised patients, lesions are more extensive, become chronic and disseminated, and the vesicles progress to form very painful ulcers (2.
The varicella-zoster virus produces disseminated lesions on the body that begin on the scalp and spread caudally; once resolved, its reactivation causes herpes zoster (shingles). This reactivation can be more severe in immunocompromised patients, potentially affecting large areas or multiple dermatomes, and may even disseminate throughout the entire body, resulting in crusts and ulcers (2).
Herpes infections in immunocompromised patients carry a worse prognosis due to the frequency of reactivation, the severity of symptoms, and the potential for dissemination. They may also cause complications such as encephalitis, hepatitis, and pneumonitis (3).
Diagnosis of herpetic infections is usually clinical, with ancillary methods used in doubtful cases. Among diagnostic tests, the Tzanck smear is a rapid and simple test for diagnosing herpetic infections in general, but it does not differentiate between different herpes viruses 4. Other diagnostic methods include antibody assays, PCR for viral DNA, viral culture, and histopathology 5).
Treatment varies according to the type of herpes infection. For non-severe herpes simplex and genital herpes, oral acyclovir may be used; whereas in severe and extensive forms, intravenous treatment with acyclovir is employed (3).
These three cases are reported due to their atypical presentation and their ability to mimic other infections such as deep fungal infections or autoimmune dermatoses.
CASE 1
A 24-year-old male patient, recently diagnosed with HIV infection and visceral leishmaniasis, was admitted to the Internal Medicine service for the initiation of treatment. He had no other underlying conditions or infections prior to this hospitalization.
He presented with lesions in the perianal and sacral regions with a 2-week evolution. These initially appeared as painful, vegetating plaques, which over time flattened and ulcerated, expanding eccentrically, accompanied by scanty serosanguineous secretion (Figure 1).
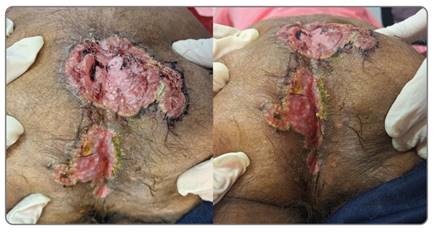
Figure 1 Large, irregular ulcerative lesions separated by healthy skin, located in the perianal region and another in the sacral region. There are no lesions on the penis
The condition is accompanied by pain of insidious onset, described as stabbing in nature, of moderate to severe intensity, worsened by physical contact, and showing little improvement with common analgesics.
General physical examination: Patient in fair general condition, conscious and oriented. Vital signs: BP 110/70 mmHg, HR 96 bpm, RR 18 breaths/min, Temperature 37.1 °C. No palpable lymphadenopathy. Abdomen soft, non-tender, with mild hepatomegaly. The rest of the skin and appendages showed no other relevant lesions.
Differential diagnoses considered include syphilitic condylomata, deep fungal infection, mycobacteriosis, and herpes infection in an immunocompromised host.
Laboratory findings: Moderate normocytic normochromic anemia (Hb: 8 g/dL), white blood cells: 3,470 cells/mm³, reactive lymphocytes: 5%, AST: 81 and ALT: 62, viral load: 3,975,542 copies HIV-1 RNA/mL, CD4: less than 40 cells/µL, and non-reactive VDRL.
A biopsy of the lesion was taken for smear, cultures, and histopathological examination. Material was also collected via scraping for PCR analysis of sexually transmitted pathogens.
The histopathology report was consistent with a herpes infection, and Herpes Simplex Virus Type 2 was confirmed by PCR. Smears and cultures for common and uncommon bacteria and fungi were negative.
The condition was classified as an atypical herpes infection. Treatment was initiated with intravenous acyclovir at 10 mg/kg/dose every 8 hours for 10 days, followed by oral acyclovir 400 mg every 8 hours to complete a 21-day antiviral course. Additionally, a diversion colostomy was performed to ensure healing and prevent superinfection.
During hospitalization, the patient received antibiotic prophylaxis with trimethoprim-sulfamethoxazole and azithromycin against opportunistic pathogens, initiated antiretroviral therapy, and completed a total dose of 20 mg/kg of liposomal amphotericin B.
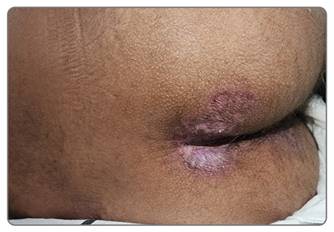
He presented for follow-up 6 weeks after completing antiviral and antiparasitic (amphotericin) treatment, having remained on full antiretroviral therapy during this period. Laboratory results showed immune improvement: CD4 126 cells/µL and viral load 500 copies/mL. Physical examination of the affected region revealed healing of the lesions (Figure 2).
The patient subsequently underwent intestinal reconstruction and continues treatment under the care of an infectious disease specialist, with good adherence to antiretroviral therapy.
CASE 2
A 35-year-old male patient with HIV, diagnosed 6 months prior, who was lost to follow-up and had not initiated antiretroviral therapy (ART). He had a history of childhood varicella, was a smoker, and had no other known chronic comorbidities.
He presented with a 1-week history beginning with unquantified, intermittent fever without a specific temporal pattern, which resolved with antipyretics. Concomitantly, sparse pseudovesicular papules appeared, distributed over the face, trunk, and extremities, some exhibiting central necrotic crusts (figure 1).
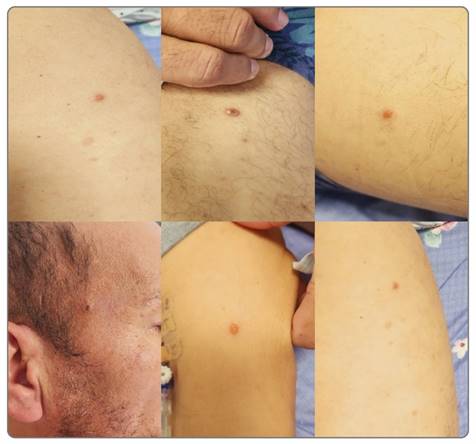
Figure 1 Presence of pseudovesicular papules, some with central necrotic crusts and others with central umbilication
Two days prior to the consultation, the patient developed yellowing of the skin and mucous membranes, prompting a consultation, and was admitted to the internal medicine ward. He denied other accompanying symptoms such as pain, malaise, asthenia, adynamia, arthralgia, or weight loss.
General physical examination: Patient in good condition. Vital signs: BP 118/74 mmHg, HR 82 bpm, RR 16 rpm, temperature 36.8 °C. Jaundice present. No clinical evidence of hepatomegaly or splenomegaly.
At the laboratory level: Hb: 10.8 g/dL, white blood cells: 3,800 cells/mm³, mixed hyperbilirubinemia (TB: 3.5 g/dL), AST: 215, ALT: 315, CD4: 56 cells/µL, viral load: 1,356,345 copies/mL, VDRL non-reactive, and hepatitis B and C negative.
Biopsies were taken for smear, culture, and histopathology under the diagnosis of molluscum contagiosum, to rule out opportunistic fungal infections. The smear and culture were negative for fungal elements, and the histopathology report showed findings suggestive of herpes infection.(figure 2).
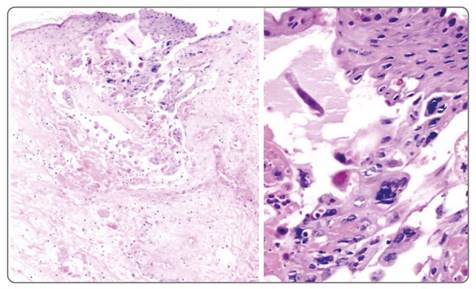
Figure 2 Epidermis showing acanthosis and intraepidermal blister formation with massive keratinocyte necrosis. Numerous keratinocytes with cytopathic changes (multinucleation, irregular nuclei, and intranuclear pseudoinclusions) suggestive of viral infection are observed
While awaiting study results, the patient experienced spontaneous resolution of the lesions and normalization of liver enzymes.
During hospitalization, the patient received prophylaxis for opportunistic infections and was discharged with the initiation of antiretroviral therapy.
Given the history of childhood varicella, and due to the morphology and location, it was classified as a probable recurrence of varicella in an immunocompetent patient. However, it was not possible to perform PCR for varicella-zoster or antibody testing.
CASE 3
A 47-year-old female patient diagnosed with Systemic Lupus Erythematosus (SLE) with renal involvement (lupus nephritis) 4 years prior, currently treated with hydroxychloroquine 400 mg/day, mycophenolate mofetil 2 g/day, and prednisone 5 mg/day. History: controlled arterial hypertension, no known prior infections. No history of childhood varicella.
She presented for consultation due to skin lesions of 1 week's duration, starting simultaneously on the face and trunk as vesiculobullous lesions of variable size, ranging from pale to intense pink in color, some with a tendency toward central umbilication. Over time, these extended to the proximal extremities and the oral and genital mucosa. The condition was accompanied by bilateral periorbital edema and intermittent, unquantified fever without a specific temporal pattern, responsive to paracetamol, present since the onset of the dermatosis. Additionally, she reported intense pain in the lesions, a burning sensation, and moderate pruritus, as well as general malaise and asthenia since the onset of symptoms. She denied taking other medications or having a history of infections.
Physical examination revealed the presence of vesicles and tense bullae on the anterior and posterior aspects of the trunk and neck, some with central umbilication. On the face, numerous honey-colored (meliceric) crusts, hemorrhagic crusts, and intact vesicles and bullae affecting the labial mucosa were observed. A positive Nikolsky sign was evident (Figure 1).
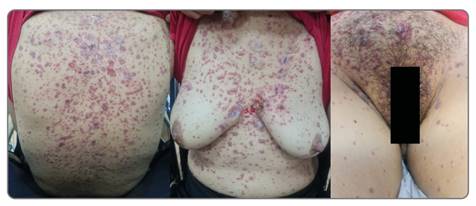
Figure 1 Numerous vesicles and bullae distributed predominantly on the trunk and face, some exhibiting central umbilication. Areas with a positive Nikolsky sign are observed on the trunk.
General physical examination: atient in poor general condition, with painful facies. Vital signs: BP 100/65 mmHg, HR 112 bpm, RR 22 breaths/min, Temperature 37.9 °C, O₂ saturation 93% on room air. Abdomen without organomegaly.
At the laboratory level: Hb: 8.7 g/dL, WBC: 15,800 cells/mm³, neutrophils: 93%, erythrocyte sedimentation rate: 8 mm/h, urea: 141 mg/dL, creatinine: 2.42 mg/dL, AST: 3797, ALT: 1443, C3 and C4 within normal limits.
Suspecting an autoimmune bullous disease (bullous pemphigoid or bullous lupus), a biopsy was performed, which returned findings consistent with a herpes viral infection (Figure 2).
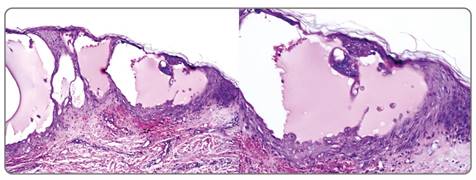
Figure 2 Epidermis showing acanthosis and hyperkeratosis. Suprabasal intraepidermal blister with the presence of necrotic keratinocytes, keratinocytes with enlarged nuclei, intranuclear inclusions, and multinucleation suggestive of viral infection. A neutrophilic inflammatory infiltrate is observed in the dermis.
Within less than 24 hours of the consultation, the patient developed acute respiratory failure with multiorgan failure and a fatal outcome; consequently, it was not possible to initiate antiviral treatment or perform studies for viral identification via molecular biology.
Given the negative history of childhood varicella and a suspected epidemiological link, the condition was classified as a primary varicella infection.
DISCUSSION
In immunocompromised patients, herpes virus infections may present with atypical clinical features, including more extensive lesions, significant ulceration, and visceral complications 3,6). In two of the three cases presented, cutaneous manifestations were severe and accompanied by visceral involvement; conversely, one case exhibited a mild cutaneous presentation associated with visceral involvement.
In the first patient, the lesions in the perianal region posed a diagnostic challenge given the broad spectrum of differential diagnoses. These include cytomegalovirus ulcers, mycobacteriosis, tuberculosis cutis orificialis, syphilis, pyoderma gangrenosum, and squamous cell carcinoma 7. It is noteworthy that herpes simplex ulcers in immunosuppressed patients may present as a co-infection with cytomegalovirus, resulting in chronic, extensive, and painful ulcers 8. The duration of treatment for herpetic genital ulcers in these patients is not strictly defined, though a course of approximately 10 days is suggested (9. In our patient, the diagnosis was achieved using conventional tests and molecular biology targeting the specific viral agent. Although testing for cytomegalovirus was not performed, the acute clinical presentation and the favorable response to acyclovir likely rule out co-infection. Regarding treatment, the course was extended to 21 days due to incomplete healing by the tenth day of therapy.
In the second case, the herpetic lesions did not have a typical distribution pattern of varicella, being isolated but distributed in various regions of the body, thus representing an atypical presentation. In immunocompromised patients, varicella may present as persistent varicella or disseminated herpes zoster, carrying a high risk of visceral involvement. However, a few cases have been reported of immunocompromised patients with a recurrence of varicella similar to the primary infection, but with few symptoms, characterized by papulovesicular lesions of generalized distribution with necrosis and central crusting. Serology is useful for differentiating a primary infection from a recurrence 10). In our patient, neither varicella-zoster serology nor DNA PCR could be performed as this was a retrospective case review; however, the history of varicella and the clinical characteristics are consistent with an atypical recurrence of varicella in an immunocompromised patient.
In the third patient, the lesions appeared simultaneously on the face and trunk, varying in size between vesicles and bullae, and exhibited a positive Nikolsky sign; therefore, the primary diagnostic impression was an autoimmune bullous dermatosis. Due to secondary impetiginization of the lesions, antibiotic coverage with ceftriaxone and vancomycin was initiated while awaiting the start of systemic corticosteroids. Unfortunately, the patient's poor general condition culminated in multiorgan failure and death, preventing further studies to determine the specific viral etiology. Given the absence of a history of childhood varicella, the condition was classified as a primary varicella infection.
The prognosis of herpes infections in immunocompromised patients is variable; however, they tend to exhibit a protracted clinical course, with a higher risk of dissemination, visceral complications, and increased mortality. It has been reported that profound immunosuppression predisposes patients to extensive and complicated presentations of herpes simplex and varicella-zoster, with an increased risk of systemic involvement and disseminated forms (3,6. Furthermore, it has been demonstrated that early diagnosis and timely initiation of treatment reduce morbidity and mortality in these patients, whereas diagnostic and therapeutic delays lead to a guarded prognosis 3. In Case 1, the patient had a favorable prognosis due to the timely initiation of antiretroviral therapy and subsequent immune recovery, achieving complete healing and a favorable outcome without complications. In Case 2, the prognosis was also good, with spontaneous resolution of the lesions and no sequelae, although his prior non-adherence to antiretroviral therapy constitutes a risk factor for future recurrences or complications. In Case 3, the prognosis was grave from the onset due to severe immunosuppression from SLE and the rapid progression of the cutaneous and systemic condition, culminating in multiorgan failure and a fatal outcome before antiviral treatment could be initiated.
The three cases illustrate the difficulty of identifying herpes infections in immunocompromised patients due to atypical clinical presentations. In Case 1, the extensive ulcerative form necessitated ruling out deep fungal infections, mycobacterioses, and malignancies. In Case 2, the sparse and disseminated lesions mimicked a molluscum-like syndrome or an opportunistic fungal infection. In Case 3, the tense bullae with a positive Nikolsky sign initially pointed toward an autoimmune bullous dermatosis . The delay in histopathological and molecular confirmation contributed to a therapeutic delay, which was particularly significant in Case 3.
STRENGTHS AND LIMITATIONS
Among the strengths of this report, which compiles three atypical clinical presentations of herpes infections in immunocompromised patients, is the description of their clinical course, morphological variability, and diagnostic complexity. Diagnostic support via histopathology in all cases, and molecular biology in one, facilitated the diagnosis. Collectively, these cases contribute valuable information to reinforce clinical suspicion in settings of immunosuppression, where dermatological manifestations may be atypical and potentially confused with other conditions.
Regarding limitations, a primary constraint is the absence of molecular confirmation in two of the three cases, which restricts etiological precision. Additionally, Case 2 presents incomplete clinical data due to the retrospective nature of the review, limiting the full characterization of the clinical picture. Finally, the fatal outcome and rapid clinical deterioration in Case 3 prevented the acquisition of further virological evidence and the performance of complementary studies that would have allowed for the definitive identification of the viral agent.
CONCLUSION
Herpes infections in immunocompromised patients may present atypically and mimic other pathologies. Early clinical suspicion, combined with rapid diagnostic methods such as the Tzanck smear and molecular tests, is fundamental for initiating timely treatment and improving prognosis. This report highlights the importance of strengthening therapeutic adherence—particularly to antiretrovirals and immunomodulators—and establishing protocols for the early recognition of these unusual presentations.
REFERENCES
1. Romero HR, Rojas PN, González LP, Klein KP, de la Parte MA, Barrios HR. Actualización en Infecciones por el Virus Herpes Simplex. Informed. 2012; 14(8):373-89. [ Links ]
2. Garza-Garza R, González-González SE, Ocampo-Candiani J. Manifestaciones cutáneas del VIH. Gac Médica México. 2014;150(S2):194-221. [ Links ]
3. Hantz S, Alain S. Infecciones por el virus del herpes simple. EMC - Pediatría. 2018;53(2):1-13. doi : 10.1016/S1245-1789(18)89722-0 [ Links ]
4. Wanat KA, Dominguez AR, Carter Z, Legua P, Bustamante B, Micheletti RG. Bedside diagnostics in dermatology: Viral, bacterial, and fungal infections. J Am Acad Dermatol. 2017;77(2):197-218. doi: 10.1016/j.jaad.2016.06.034. [ Links ]
5. Navarrete Cuadrado KS, Mastrodomenico Vargas M, Guao Salinas H, Ruiz Pérez O. Varicela zóster. Biociencias. 2020;15(1):79-89. doi:10.18041/2390-0512/biociencias.1.6364 [ Links ]
6. López Villaescusa MT, Martínez ML, Faura Berruga C, Pérez García L. Herpes Zoster diseminado. Rev Clínica Med Fam. 2012;5(1):64-6. doi: 10.4321/S1699-695X2012000100012. [ Links ]
7. Re Domínguez M, Jara E, Barboza G, Ortiz B, Masi M, Domínguez O, et al. Perianal herpetic ulcers in immunosuppressed patients. Report of two cases. Our Dermatol Online. 2017;2(8):189-94. [ Links ]
8. Azuaje C, María A, Aguilar C, Enrique L, Ucelo Q, María Z, et al. Úlcera perianal secundaria a coinfección por virus herpes simple y citomegalovirus. Enf Microbiol 2020;40(41):155-158. [ Links ]
9. Gouveia AI, Borges-Costa J, Soares-Almeida L, Sacramento-Marques M, Kutzner H. Herpes simplex virus and cytomegalovirus co-infection presenting as exuberant genital ulcer in a woman infected with human immunodeficiency virus. Clin Exp Dermatol. 2014;39(8):915-7. doi: 10.1111/ced.12453. [ Links ]
10. Bolte C, Tapia G, Sazunic I. Recurrencia atípica de la infección por el virus varicela zóster en un paciente inmunodeprimido. Piel. 2017;32(4):198-200. [ Links ]
Responsible Editor: Prof. Dr. Hassel Jimmy Jiménez, https://orcid.org/0000-0003-4078-5853; Dra. Lourdes Talavera, https://orcid.org/0000-0001-9671-3037.
Authors' contributions: EJIF and CAGB prepared the manuscript. ABFAC reviewed and approved the final version of the text. CMB performed the histopathological studies and participated in the revision of the manuscript.
Received: January 23, 2025; Accepted: December 09, 2025
 Este es un artículo publicado en acceso abierto bajo una licencia Creative Commons
