



 Inglés (pdf)
 Articulo en XML
 Referencias del artículo

 Traducción automática
 Enviar articulo por email
 Citado por SciELO
 Similares en
SciELO

 Permalink


INTRODUCTION
The HER2 oncogene, a member of the human epidermal growth factor receptor (HER/EGFR/ERBB) family, has been implicated in the pathogenesis of various cancers, including ovarian cancer. Its role in ovarian cancer is complex, as HER2 can be overexpressed in a subset of ovarian tumors, influencing tumor behavior and patient prognosis. Studies indicate that HER2 expression in ovarian cancer varies significantly, with reported overexpression rates ranging from 5% to 66%1,2,3. This variability suggests that HER2 may not only serve as a prognostic marker but also as a potential therapeutic target. The mechanisms by which HER2 contributes to ovarian cancer progression involve its ability to regulate cell proliferation, differentiation, and apoptosis. HER2 overexpression can occur in both the cell membrane and the nucleus, and in the latter, it has been associated with a worse prognosis for example in breast cancer, including shorter survival times and increased rates of relapse4. The receptor can be detected both on the cell membrane (mHER2) and in the nucleus (nHER2), which is mainly mentioned in breast cancer studies. The frequency of mHER2 in this neoplasia is 15-20%, while the presence in the cell nucleus is variable and the cases are generally mHER2 negative5,6,7. The presence of HER2 in the nucleus responds to a canonical and translocation mechanism, although its clinical relevance is still under study8. Also HER2 overexpression in ovarian cancer has been linked to enhanced tumor aggressiveness and resistance to conventional therapies, underscoring the need for targeted treatment strategies9. Furthermore, the presence of HER2 mutations and polymorphisms, such as the Ile655Val variant, has been noted in ovarian cancer patients, suggesting that genetic alterations may also play a role in the oncogenic potential of HER2 in this context10,11. Targeting HER2 in ovarian cancer has gained traction in recent years, with therapies such as trastuzumab and neratinib showing promise in preclinical and clinical settings. Trastuzumab, a monoclonal antibody that inhibits HER2 signaling, has demonstrated efficacy in HER2-positive ovarian cancer cell lines and has been associated with improved outcomes in patients with high HER2 expression3,12. Additionally, the combination of HER2-targeted therapies with other agents, such as taxanes, has been explored to enhance treatment efficacy13. Recent studies have also investigated novel therapies such as the use of enzymatic liposomes with anti-Her2 activity and also new versions of trastuzumab which may provide a new avenue for treatment in HER2-positive ovarian cancer14,15. In summary, HER2 plays a significant role in the biology of ovarian cancer, influencing tumor behavior and treatment responses. The variability in HER2 expression and the potential for targeted therapies highlight the importance of personalized medicine approaches in managing ovarian cancer. Continued research is essential to fully elucidate the mechanisms underlying HER2's role in ovarian cancer and to optimize therapeutic strategies targeting this oncogene.
Therefore, the aim of this study was to analyze the subcellular expression of the HER2 oncogene-particularly its nuclear localization-in ovarian cancer and benign tumor samples, using immunohistochemistry, in order to assess its potential as a diagnostic or prognostic biomarker.
MATERIALS AND METHODS
Patient samples
During the period between the years 2021 and 2024, a retrospective study of 47 samples from patients with ovarian cancer and cystoadenome (benign tumor), fixed in formalin and embedded in paraffin, from the Anatomy-Pathology Service of Angela Llanos and JR. Vidal Hospital, belonging to the Ministry of Public Health of the city of Corrientes, Argentina was carried out. Cases with necrosis greater than 30%, hemorrhage, scarce sample, or lack of data were excluded. In addition, through a form, epidemiological and clinical and anatomo-pathological information was collected. The samples were histologically classified as benign tumors and cancer in the Pathological Anatomy services of the hospitals and were randomly selected. In all cases an informed consent was obtained observing Law 25326 of Personal data protection. The project was approved by the Ethics Committee of the Hospital JR Vidal and Ethics Committee of the School of Medicine (Resolution No. 9/15).
Immunohistochemistry (IHC)
The detection of HER2 was carried out in the laboratory of the Faculty of Medicine, National University of the North East. From tissue fixed in formalin and embedded in paraffin, 2 microns cuts were made. After deparaffinizing and hydrating with Xylol and decreasing graduation alcohols, antigenic exposure was performed with Proteinase K (Bioamerica PKB4100) pH8 (10ug/ml). It was incubated overnight with ErbB-2 (HER2) monoclonal antibody (3B5- MA5 13675 thermo fisher, RRID: AB_10985617). It was then incubated with anti-mouse/anti-rabbit and Streptavidin (Vectastain® Elite® ABC universal Kit PK-7200). It was revealed with DAB (sustrate kit cell marque 957D-20) and counterstaining with Hematoxylin (GILL II solution Biopack 9491.07) was performed.
A breast cancer sample was used as a positive control for HER2. A negative control was used in each experiment (which does not carry the primary antibody, RRID: AB_2922376). Immunostaining was assessed by three individuals (M.A.C, H.M.M. and L.R.) who were unaware of the clinicopathologic variables. Differences in opinion were resolved by a common reading. Each slide was carefully examined in the light microscope at 400x magnification in the area of the tumor that contained the greatest fraction of positively stained cancer cells, and a minimum of 100 cells per specimen were counted.
To quantify, a scoring system was previously used, taken from the American Society of Clinical Oncology/College of American Pathologists (ASCO/CAP) for membrane HER2 in breast cancer16 and the scoring system used by Schillaci et al. (17) for detection of HER2 in the cell nucleus.
Data Analysis
The clinical and epidemiological data collected were statistically analyzed with Graphpad Prism 6 (RRID:SCR_002798) and SSPS programs. The correlation between the variables was performed using the chi square test and the value of p≤0.05 was considered statistically significant. The Office Excel program was used for graphics design.
RESULTS
Of the 47 samples analyzed, 40.4% (N=19) of the cases correspond to high-grade carcinoma, the other samples (N=28) were distributed in the different phenotypes of ovarian tumors to low-grade including 8 cases of benign phenotype (Table A by Figure 1).
The detection of Her2 was carried out, both in the cell membrane (MHER2) and in the nucleus (NHER2) and the scoring systems were applied according to references described previously.
The Figure 1B shows the expression of HER2 in the cytoplasmic membrane tested by IHC in 47 samples, with a distribution of 5% of HER2 positive cases (3+), 23% equivocal (2+) and 72% tested negative (1+ and 0). The observation was carried out by independent observers and the kappa index is 0.616, this was considered to be a good agreement (Table 1C).
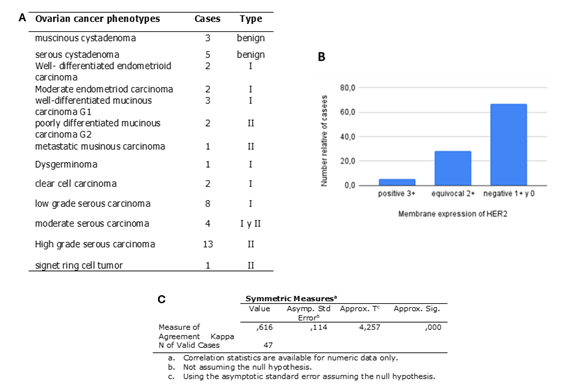
Figure 1: Table of ovarian tumor phenotypes (A) and analysis of HER2 expression on the cell membrane (B). The observation was carried out by independent observers and the kappa index is between 0 and 1, being 0.616 (C).
The presence of the receptor in the nucleus was analyzed in the two groups of cancer cases type I and type II, and in the group of benign tumors, finding a significantly higher frequency in the groups with malignant phenotypes or cancer itself in contrast to the benign tumor that tested negative (Figure 2C). Our results show that HER2 is present in the nucleus, 20.5% in cancer type I and 25.6% in cancer type II. The cancer type II being highly significant with respect to the benign tumor (Table 2D).
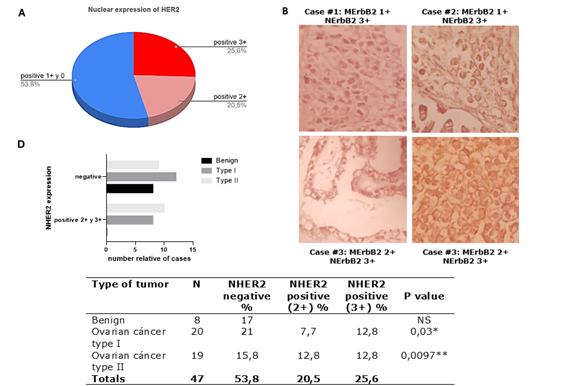
Figure 2: Analysis of HER2 expression. A) in the core of 47 samples (including cancer cases and benign phenotypes). B) 4 representative cases of IHC are shown. 400X magnification. C) Correlation Analysis of NHER2 expression and benign tumor, type I and II cancer in 47 cases. The Fisher's exact test was used Type I vs Benign *P=0.03 and Type II vs benign **p=0.0097. D) Table of NHER2 dates full.
DISCUSSION AND CONCLUSIONS
Increased expression of the Her2 receptor was observed in ovarian cancer samples, particularly in the nucleus, which coincides with surveys of the receptor in this neoplasia18,19. The observation of HER2 in the nucleus was widely mentioned in molecular studies of breast and gastric cancer20,21,22, but in other types of cancer no nuclear overexpression was found23,24.
The detection in the cytoplasmic membrane was not conclusive since the majority of the positive cases were considered “equivocal” so in those cases the study should be repeated in another sample in order to define the presence of Her2, according to the ASCO/CAP criteria16. It should be mentioned that these criteria are specific to breast cancer and there is currently no guide for ovarian cancer analysis. However, the analysis in the cell nucleus revealed a high frequency of HER2, which is unconventional and could have implications for prognosis, therapeutic resistance and the design of new diagnostic markers5,24. This receptor appears in the nucleus by endocytosis and translocation, a canonical mechanism, although retrograde transport of its isoforms would exist as an alternative mechanism in triple-negative breast cancers (8). Although its clinical relevance is under study, it is proposed that once in the nucleus, it can bind to transcriptional activators that activate genes that would favor the progression to cancer5,6,25.
On the other hand, the comparison between samples of benign tumors and different types of ovarian cancer, in terms of receptor expression, showed a higher frequency of Her2 in ovarian cancer samples, which coincides with current research26,27; while in the benign tumor samples there was no detection. This finding would also indicate a possible participation of Her2 in oncogenesis.
Although the number of samples analyzed is small, increased expression of Her2 could be observed in ovarian cancer tissue, suggesting the participation of this receptor in oncogenesis, as already described in other tumors such as breast, kidney, gastric cancer, among others28,29. A subsequent study of a larger cohort and the application of the PCR technique would allow for better validation of the results, especially in HER2-negative cases.
We can also conclude that the presence of Her2 in the nucleus could be taken as a reliable indicator to be used in diagnosis and perhaps also when evaluating prognosis, considering that a marked expression was observed in accordance with the malignancy of the sample analyzed.
Furthermore, the overexpression of Her2 is related to resistance to conventional treatments, highlighting the application of specific therapy such as the use of monoclonal antibodies that inhibit Her2 signaling (trastuzumab), and at the same time evaluate new target markers27,30.
These are the first contributions of a larger work that includes the analysis of Her2 in different types of gynecological cancers, such as those of the cervix, vulva, vagina and ovary, in which this receptor would play a fundamental role in oncogenesis and demonstrate its overexpression would allow evaluating the treatment, survival and prognosis of this pathology. We highlight the value of this study in a public hospital setting in Argentina, providing evidence from a region with limited molecular information on oncology.

